University Medical Center Getting New Lab in Southern Nevada

University Medical Center Getting New Lab in Southern Nevada

A new clinical lab being built by Nevada Health and Biosciences Laboratory in conjunction with University Medical Center of Southern Nevada (UMC) is expected to open in early 2027. The 34,000-square-foot lab will initially employ about 35 people and will significantly expand UMC’s current test offerings. Laboratory Economics recently spoke with Deb LaCava, Administrative Director of Laboratory Services at UMC.

Tell me about the new Nevada Health and Biosciences Academic Laboratory.
It’s located in the Las Vegas Medical District and will significantly expand UMC’s capacity while supporting education, research and future transplant-related services. When we first open, we will be moving our molecular and microbiology labs from the main hospitals into that building and expanding both. We’re having a BSL-3 lab built into that facility, so that will expand our capacity in microbiology. We’ll also be bringing in toxicology and drug testing. We’ll have mass spec, and we also are planning an HLA lab for transplants.
What was the impetus for the new lab?
Medical care is lacking in Nevada compared to our neighboring states. A lot of patient testing must be sent out of state to reference labs, and that really delays patient care. Our new lab will get results to patients in a couple of hours instead of seven or eight days.
Where is the majority of testing done now?
Routine testing is generally performed in the hospital lab. More specialized tests, such as NGS or specialized panels, are sent out to a reference lab such as Labcorp or Quest.
What geographic areas will the new lab serve?
Initially, it will serve the Las Vegas Valley. I’ve had calls from Arizona and California labs asking us to do testing for them, so once we’re set up and ready, we’ll expand our range. Some of it has to do with licensing. Not every state requires a license, but California does.
How many clients are you currently serving, and do you expect that to increase with the new lab?
Outside of the UMC hospitals, we have about 14 reference clients that send us testing on an almost daily basis. It accounts for about $1 million of testing per year. I anticipate getting more clients once the new lab is open. We anticipate increasing the testing for our UMC patients as well, as they represent the biggest client population for the lab.
Do you expect your volume to increase substantially?
Right now, our lab runs about 7.5 million tests per year—mostly inpatient testing. Between molecular and microbiology, we run just under 2 million tests per year. We’re hoping to initially add at least another 500,000 in that first year. I anticipate adding volume each year for the first three or four years.
How will the new lab improve turnaround times?
Right now, specialized testing is sent to a reference lab. Most of them are out of state, such as California, Arizona and the East Coast. This causes delays just for transit times. And because of batch testing, some of the labs may only perform a test two or three days per week. So right now, any testing that’s sent out of state is averaging five to 10 days turnaround time. If we do the testing here, we can give the physicians 24-hour maximum turnaround time with most test results reported in four to six hours.
What else will the new lab offer?
We’ll have a BSL-3 lab. We are already the designated hospital if there’s an Ebola case here in town. We’ll also be able to do tuberculosis confirmation and some other tests, such as Zika. The big part of this will be the HLA lab. Once that opens, we’ll be supporting our own transplant program. We’ll also be able to support platelet matching for patients who need blood transfusions and surgeries.
How will this lab affect workforce development in Southern Nevada?
We plan on adding several full-time employees when the lab first opens, and as we grow, we’ll likely add more. I think the biggest contribution to the workforce will be the training we’ll be able to provide for future lab professionals. They’ll be able to have hands-on experience in a state-of-the-art lab.

How many med tech students are you training right now?
We generally have four rotating through our labs at any given time. We train them for eight weeks. With the added space and staff in the new lab, we’ll be able to train 2-4 more per year.


New Bill Would Expand Price Transparency Requirements to Independent Labs

New Bill Would Expand Price Transparency Requirements to Independent Labs

The Patients Deserve Price Tags Act would significantly impact independent labs by bringing them under the same strict federal price transparency mandates that currently apply only to hospitals. Versions of the bill were introduced late last year in the Senate (S. 2355) and House (H.R. 5582). The bill would require independent labs to make monthly public disclosures of their negotiated reimbursement rates across their entire test menu. “The reporting requirements in the current draft are staggering,” stated the American Clinical Laboratory Association (ACLA) in a July 2 letter to Senate leaders.

New Bill Would Expand Price Transparency (cont’d from page 1) The champions behind the bipartisan Patients Deserve Price Tags Act are U.S. Senators Roger Marshall (R-KS) and John Hickenlooper (D-CO). So far, the proposed legislation has the support of a total of 24 Senators and 12 members of the House.

“Customers don’t walk into a restaurant only to find out how much the food costs when they get the bill. Patients should know the price of the service they need before they make any decisions,” according to Senator Marshall.

“We deserve to know exactly what we are paying for whether it’s a lab test, a colonoscopy, or an
MRI,” stated Senator Hickenlooper.

The Senate Committee on Health, Education, Labor, and Pensions (HELP) held a full committee hearing on the bill on March 19, 2026. In addition, the House Energy and Commerce Health Subcommittee held a hearing on June 10, 2026.

Effective July 1, 2027, the bill would require the following disclosures from all CLIA-certified clinical and anatomic pathology labs:

  • Public Rate Sheets: Labs must make publicly available, and update monthly, all negotiated rates with health insurance plans for all lab tests and ancillary services they offer.
  • Cash Discounts: Labs must explicitly disclose their standard discounted cash prices for patients paying out-of-pocket.
  • Standardized Descriptions: Lab tests must be listed with plain-language descriptions and standard billing codes so consumers can easily compare prices across different facilities.

Furthermore, labs that fail to post their rates or try to hide fees will face heavy financial penalties and enforcement actions under the proposed legislation. Labs that fail to comply are subject to a civil monetary penalty (CMP) of up to $300 per day. And the bill gives the U.S. Secretary of Health and Human Services (currently Robert F. Kennedy Jr.) the authority to increase the penalty starting in 2028.

In the letter to Senate leaders, ACLA President Susan Van Meter noted that there are more than 2,100 test codes on the Medicare Clinical Laboratory Fee Schedule alone and that some ACLA member labs have contracts with up to 900 health plans. Thus, the bill would require some large labs to review and post nearly two million rates each month (i.e., 2,100 codes x 900 plans). The reporting costs to meet this obligation would be significant and divert resources away from patient care, according to Van Meter.

“A far more reasonable approach—and one that would yield information that is truly useful to patients—would be to require clinical labs to post cash prices for those testing services on the CMS list of shoppable services,” according to Van Meter. There are currently 14 routine clinical lab tests specified in the CMS core list of 70 mandatory shoppable services.

Hospital Price Transparency

The Patients Deserve Price Tags Act also seeks to expand existing transparency requirements for hospitals. For example, the bill requires hospitals to update and post publicly their rates each month, rather than the current requirement of once a year. In addition, the bill dramatically increases penalties and mandates CMPs for every violation, removing CMS discretion. Under the

bill, for example, hospitals with more than 500 beds, would be subject to a $25 per bed per day fine (i.e., $12,500+ per day) for noncompliance.

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

Laboratory Economics has just released The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028. With this special report, you can tap into 100+ pages of proprietary market research that reveals critical data and information about key business trends affecting the anatomic pathology market.

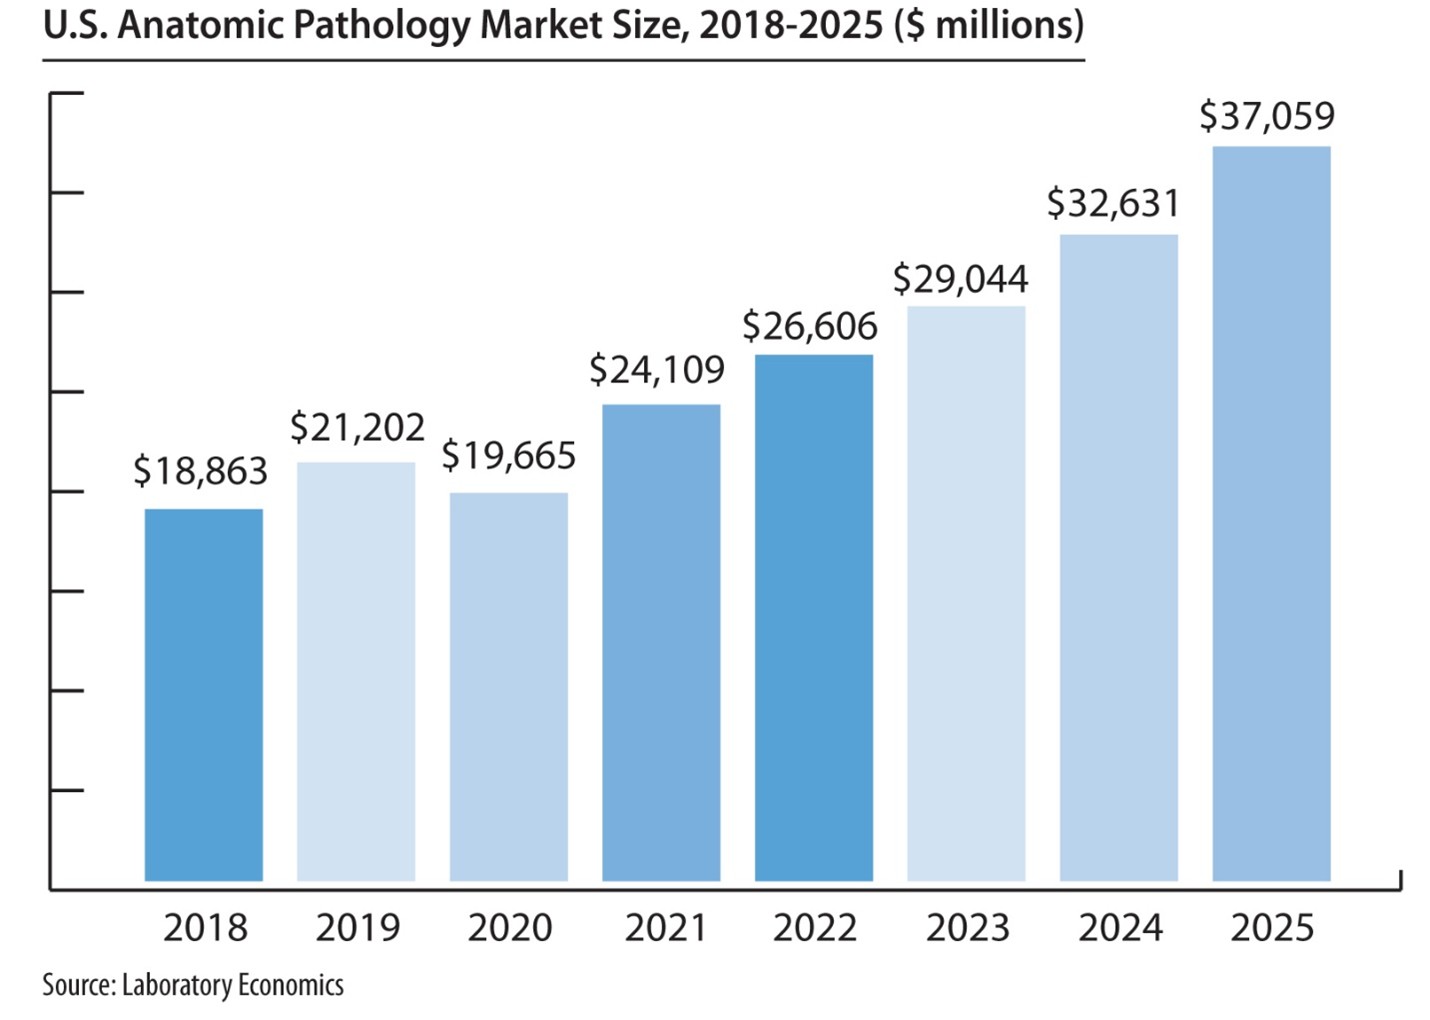
The report reveals that the U.S. anatomic pathology market represented an estimated $37.1 billion of revenue in 2025 with a long-term annual growth rate of 10.1%. Growth is being driven almost entirely by increased molecular oncology testing, especially minimal residual disease (MRD) testing to monitor cancer treatment.

The U.S. anatomic pathology market faces unprecedented change, including the introduction of artificial intelligence tools that increase pathologist productivity, greater utilization management by private payers and persistent reimbursement pressure.


“The introduction of new higher-priced molecular oncology tests, including next-generation sequencing for tumor mutation profiling and MRD testing, should more than offset price and volume pressure on routine pathology tests,” according to Jondavid Klipp, President of Laboratory Economics.

In addition, the growing adoption of digital pathology and application of AI software tools to digitized slide images have the potential to profoundly change the way pathology is practiced within the next 3-5 years.

The greatest challenge comes from third-party payers, which are instituting prior authorization policies and laboratory benefit management programs designed to lower utilization of anatomic pathology services and genetic tests for cancer.

The report includes:

  • More than 100 charts and graphs
  • Pathology market size and growth rates
  • Detailed estimates for market subsets like uropathology, dermatopathology, and gastrointestinal pathology
  • In-depth analysis of the molecular oncology testing market size and growth rates
  • Medicare claims data for 60+ key pathology codes covering surgical pathology, molecular oncology, immunohistochemistry and special stains, tumor marker immunoassays, FISH testing and flow cytometry
  • Cervical cancer testing trends and pricing data
  • Detailed analysis of the emerging digital pathology & AI market
  • Results from Laboratory Economics Anatomic Pathology and Clinical Lab Trends Surveys from 2015 through 2025

Anatomic pathology companies highlighted include:

  • Adaptive Biotechnologies
  • Bako Diagnostics
  • Caris Life Sciences
  • CellNetix Pathology & Laboratories
  • Exact Sciences
  • Foundation Medicine
  • Fulgent Genetics/Inform Diagnostics
  • Guardant Health
  • Labcorp
  • Mayo Clinic Laboratories
  • Myriad Genetics
  • Natera Inc.
  • NeoGenomics
  • OPKO/BioReference Labs
  • PathGroup
  • Quest Diagnostics
  • Sonic Healthcare/Aurora Diagnostics/ProPath Services
  • Tempus AI
  • Versant Diagnostics

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028 is published by Laboratory Economics (http://www.laboratoryeconomics.com), an independent market research firm focused exclusively on the business of pathology and laboratory medicine. Report author Jondavid Klipp has been covering key business trends affecting clinical lab testing and anatomic pathology services for 27 years.


How to Keep Your Existing LDTs on the Market

How to Keep Your Existing LDTs on the Market

How to Keep Your Existing LDTs on the Market

Labs have some tough decisions to make now that the FDA has issued a final rule giving it authority to regulate LDTs. Labs offering LDTs prior to publication of the final rule on May 6 have three choices: 1) comply with the new FDA regs and keep their LDTs on inhouse test menus; 2) switch to an FDA-cleared test kit (if available); or 3) ignore the FDA regs and risk potential enforcement actions and fines. For expert advice on option 1 from regulatory attorney Christine Bump.

Christine Bump, a regulatory attorney at Penn Avenue Law & Policy (Washington, DC), has been guiding laboratories and test manufacturers through the FDA’s premarket clearance process and post market compliance requirements for 20 years. Below we summarize Bump’s
advice for keeping existing LDTs on the market.

FDA Stage 1 requirements for currently marketed LDTs
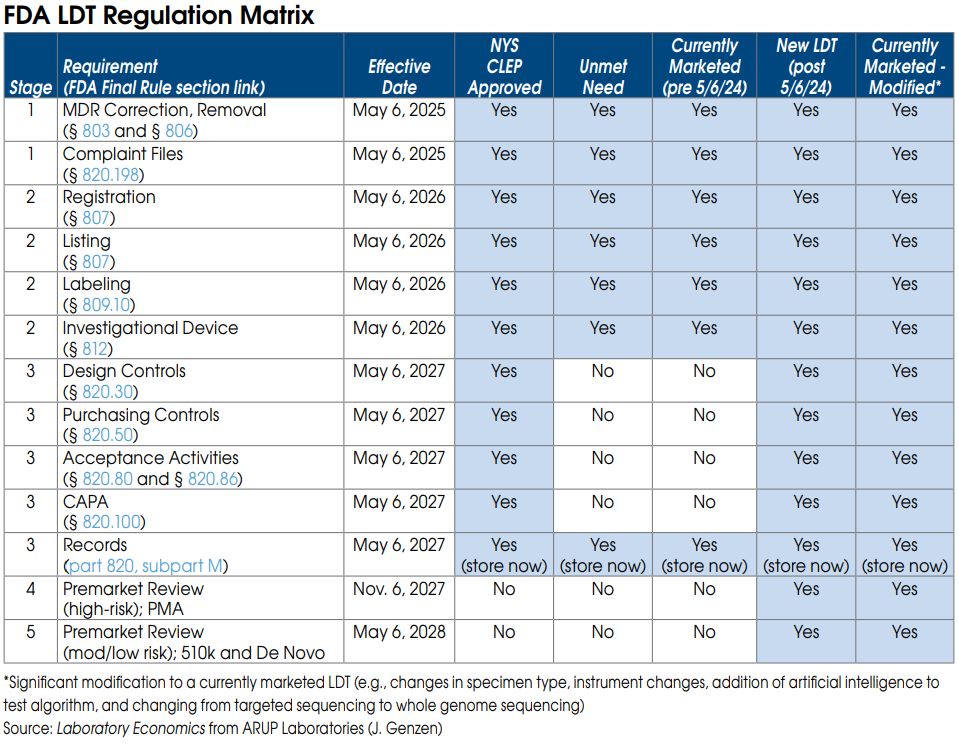
Nearly all LDTs, including currently marketed LDTs (prior to May 6, 2024), “unmet need” LDTs performed by “integrated” health systems and NYS CLEP-approved tests, must meet Stage 1 requirements by May 6, 2025.

Stage 1 includes FDA Medical Device Reporting (MDR), which will require laboratories to report adverse events for any LDT that they perform. Under FDA’s regulations, an adverse event is any event that reasonably suggests that a device has or may have caused or contributed to a death or serious injury, or would be likely to cause or contribute to a death or serious injury if the event happens again. An adverse event report would therefore be required for an incorrect test result that has, may, or could cause such consequences. The incorrect test result could be caused by instrument malfunctions as well as mislabeled or contaminated specimens.

An adverse event report must generally be reported to the FDA within 30 days after the lab became aware of the error. The regulations require specific information be included in the report, and labs will also need to file\ a report that describes what corrective action they took, or if they chose to remove that LDT from their test menu.

An adverse event report could prompt the FDA to ask follow-up questions or schedule an on-site inspection.

The FDA is especially sensitive to incorrect test results that delayed patient treatment or caused
unnecessary treatment (or had the potential to do so).

Stage 1 also requires labs to maintain complaint files for each LDT they offer, including the date the complaint was received; the name, address, and phone number of the complainant; the nature and details of the complaint; any corrective action taken, etc. Specific records and reports
must also be maintained and submitted regarding corrections and removals of tests, including for
repairs, adjustments, relabeling, etc.

FDA Stage 2 requirements for currently marketed LDTs
Once again, Stage 2 requirements apply to nearly all LDTs and become effective May 6, 2026.

Stage 2 requires each laboratory to be registered with the FDA and list all of the LDTs they perform.

Stage 2 also requires labs to submit labeling for each LDT they offer. Labeling includes test performance information and a summary of supporting validation. As part of its review of labeling, the FDA plans to look closely at claims of superior performance and whether those claims are adequately substantiated. This includes any test claims made on a lab’s website, brochures or by sales reps.

Labeling information is typically included as a package insert or affixed to test kit box for FDA-cleared or approved IVD tests. However, since LDTs are not distributed in boxed test kits, it is unclear exactly where the label for an LDT will need to be placed. Labels might be required on the LDT test requisition form, but this hasn’t been confirmed yet. We’re waiting for the FDA to issue more guidance on label requirements.

FDA Stage 3 requirements for currently marketed LDTs

By May 6, 2027, currently marketed as well as “unmet need” LDTs developed and used within “integrated” health systems need to be in compliance with the records requirements of the quality system regulation. These records relate to the device master record, the device history record, and the quality system record. (Note: Complaint file record requirements are already covered under Stage 1.)

The device master records must include information about device specifications, production process specifications, quality assurance procedures and specifications, packaging and labeling specifications, and procedures and methods for installation, maintenance, and servicing.

The device history records must include information about the dates and quantity manufactured, the quantity released for distribution, acceptance records, information to identify each production unit and device identifiers.

Labs must have the required information compiled, documented, and in a records system that is accessible and readily available to FDA investigators during inspections.

FDA On-site Inspections
All registered lab facilities performing LDTs are subject to scheduled on-site inspections by the FDA every two years. FDA inspections are completely different than and are independent of CMS CLIA and CAP inspections. FDA inspectors will be focused on reviewing LDT test records and files. However, the reality is that the FDA already lacks the resources to perform regularly scheduled on-site inspections of existing test kit manufacturers. The agency may have difficulty keeping up with the thousands of new lab facilities that fall under its purview as a result of its final rule. 

Google Releases AI Tool for Pathology

Google Releases AI Tool for Pathology

Google Releases AI Tool for Pathology

Google has released a free cloud-based tool (“Path Foundation”) that 
transforms digitized slide images into numerical data that researchers 
can use to create AI tools for pathology. “This is a landmark for us,” says 
David Steiner, MD, PhD, Clinical Research Scientist at Google. Based on  feedback to Path Foundation, Google will make decisions toward  developing commercial AI tools for pathologists. 

For more than seven years, Google has employed a team of clinical research scientists based in Mountain View, California and London, England, tasked with developing AI software tools for radiology and pathology. Below is a summary of LE’s interview with Google’s David Steiner, MD, PhD, Clinical Research Scientist.

How can labs and pathologists use Path Foundation?

Commercial labs and academic medical centers, for example, can use Path Foundation to convert patches of their digitized slide images into numerical vectors, known as embeddings. These embeddings capture important features and patterns contained in digitized slide images which are learned by Path Foundation during its training on millions of pathology images. After the embeddings for each image are collected, this data can be used to train and create custom algorithms for a range of tasks such as identifying tissue type, tumors, or performing quality assurance on digitized images.

What’s the benefit of using a “Foundation” model to analyze content in images?
Leveraging the embeddings from Path Foundation requires less data and computational resources than traditional methods, giving researchers a big head start toward developing their own algorithms.

In contrast, traditional methods such as strongly supervised deep learning models require more resources because every task requires fresh training in its own unique deep learning model and many labeled images for each category of interest.

The foundation model is similar to that of seasoned guitar player quickly learning a new song by ear. Because the guitar player has already built up a foundation of skill and understanding, they can quickly pick up the patterns and groove of a new song.

Where did you get the digitized images to train Path Foundation on?
We used 20,000 whole-slide images, covering millions of image patches, from a variety of sources, including the National Cancer Institute’s Cancer Genome Atlas, as well as academic medical centers and some private pathology labs.

What is the user roadmap to getting started with Path Foundation?
After filling out the access form, users can run a small demo notebook that walks them through how to train a tumor classifier. To use Path Foundation on their own task (i.e., identifying tissue type) they would need to collate a set of digital pathology images with accompanying labels. The user would then upload these images and labels into Google Cloud.

From there, the users can adapt the demo notebook to call the Path Foundation API on their uploaded images. Using the existing code in the demo notebook they would then train a model to classify their images based on the labels and evaluate its performance on a held-out part of
the dataset not used to train the model. In the future we hope to make it even easier to use Path Foundation and the embeddings directly in your pathology slide viewer with no coding required.

We’re offering Path Foundation free to users on github.com/Google-Health.

Do labs that use Path Foundation need to share their digitized images or the results of their research with Google?
They don’t need to share the images or the results of their research with Google. They do need to have their images stored in Google Cloud (in their own private or institution account), but these are kept private to the user and not accessible by Google. In addition, when the images are sent to the Path Foundation model to compute the embeddings, they are not saved or stored by Google.

Any plans to develop commercial AI software tools like Ibex, Paige or PathAI?
Yes. Path Foundation represents a landmark toward that end.

What is the next step for your research team in terms of developing AI tools for pathologists?
We’ll take feedback on users from Path Foundation to understand key-use cases and how to make the tool better and easier to use. We’ll also explore how these embeddings might be used with large language and large multimodal models (LLMs & LMMs). And then we plan to develop useful approaches and models for working with whole slide images (WSIs), in addition to the “patch-based” models and applications that this current tool represents.

Has Google completed any studies related to AI-assisted diagnostic tools for cancer?
Yes. We have published several studies in peer-reviewed journals.

Most recently, we published a study that used AI to predict immunotherapy outcomes from digitized slide images in non-small cell lung cancer (Cancer Research, vol. 84, 2024).

In 2023, we published a paper that showed how AI can be used for clinical decision-making in colorectal cancer (Nature Communications Medicine, vol. 3, 2023). And, in 2022, we published a study that used AI for diagnosis and Gleason Grading of prostate cancer (Nature Medicine, vol. 28, 2022).

We have also published studies focusing on AI models for breast cancer.

Will AI algorithms eventually replace pathologists?
AI will make pathologists better rather than replace them. Initially, AI will be used to automate repetitive tasks such as locating the image patches that pathologists should focus their eyes on. Eventually, AI could be used to query images. Pathologists and researchers may someday be able to
type in specific questions and get AI answers about an image.

Is there the potential to integrate pathology and radiology image data using AI?
I’m excited to explore this and do see the promise in bringing these two specialties together. I believe the combination will yield more than the sum of the parts. Google does have a team of research scientists working on AI tools for radiology. And we did introduce an AI tool for chest x-rays (CXR Foundation) in July 2022.

BioReference Labs Goes Live With Digital Pathology Plus AI

BioReference Labs Goes Live With Digital Pathology Plus AI

BioReference Labs Goes Live With Digital Pathology Plus AI

OPKO’s BioReference Labs (Elmwood Park, NJ) went live in December with new whole-slide imaging scanners from Leica Biosciences (Buffalo Grove, IL). The scanners have been integrated with a digital pathology solution, PathFlow, made by Gestalt Diagnostics (Spokane, WA). PathFlow is a cloud-based software system that has helped integrate BioReference’s LIS, workflow and scanned slide images with artificial intelligence algorithms developed by MindPeak (Hamburg, Germany). BioReference is also using PathFlow for slide image management and archival storage.

BioReference is using MindPeak’s AI tool (named BreastIHC) to detect and quantify breast cancer cells from digitized slide images with immunohistochemistry at its main laboratory in northern New Jersey. Pathologists can access their case and slide images securely on their computer monitors and use their mouse to outline regions of interest (ROI). All cells within this outlined ROI are instantly classified into positively stained tumor and unstained tumor cells. The panel of algorithms include five key tumor markers (ER, PR, Ki-67, HER2, and P53) which can be counted and scored.

Eventually, Dan Roark, Chief Executive Officer, Gestalt Diagnostics, expects the AI algorithms to both automatically identify the regions of interest in addition to performing IHC marker positivity scoring.

Digital Pathology & AI Market Growth
Separately, Roark says that after more than 10 years of limited adoption, digital pathology is finally starting to take off in the clinical market in the United States. Whole slide scanners have gotten quicker and less expensive. For example, it used to take 8-10 minutes to scan a slide but now takes as little as 30 seconds. But the biggest driver is the pathologist efficiency gains obtained when AI is applied to digitized slides. “The number of RFP requests we receive is exploding,” says Roark.

Worldwide Opportunities for U.S.-Based Pathologists
The U.S. has more working pathologists per capita than most other countries. For example, there are approximately 20,000 actively practicing pathologists in the United States, according to the American Medical Association. This works out to a ratio of one pathologist for every 17,000 people.