Nursing Home Labs Will Be Hurt the Most from Medicare Rate Cuts

Nursing Home Labs Will Be Hurt the Most from Medicare Rate Cuts

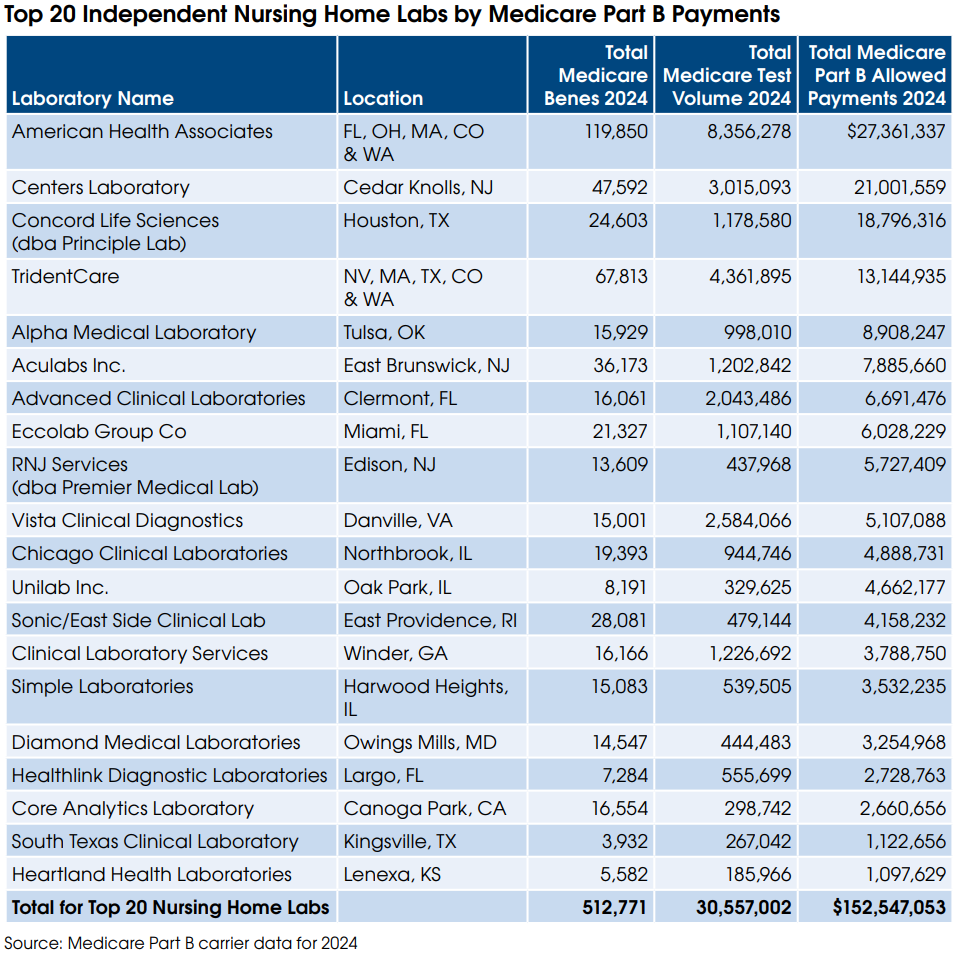
The nation’s biggest independent nursing home lab company, American Health Associates (AHA —Davie, FL), might be the single lab hurt the most if the preliminary Medicare CLFS rate cuts are finalized effective for 2027-2029. AHA, whose main labs are located in Florida and Ohio, provides lab testing services to more than 2,000 nursing homes and long-term care facilities in 23 states.

AHA gets roughly 25% of its total ~$100 million in annual revenue directly from the Medicare CLFS.

AHA is currently going through a Chapter 11 bankruptcy reorganization (see LE, May 2026).

Other independent nursing home lab companies with significant Medicare Part B revenue include Centers Laboratory (Cedar Knolls, NJ), $21 million; Principle Lab (Houston, TX), $19 million; and TridentCare (Hunt Valley, MD), $13 million.

PAMA Delay Included in New Spending Law

PAMA Delay Included in New Spending Law

PAMA Delay Included in New Spending Law

On Feb. 3, President Trump signed into law a $1.2 trillion spending
package. Included in the Consolidated Appropriations Act of 2026 is a freeze in Medicare CLFS rates through December 31, 2026. In addition, the new law modifies the private-payer data collection and reporting period for labs. Labs will now have to collect their private-payer payment data from January 1 – June 30, 2025, and report it to CMS between May 1, 2026 – July 31, 2026. CMS will use this data to calculate CLFS rates for 2027. “This is welcome relief, but what we really need is permanent reform,” says Erin Morton, Washington Representative for the National Independent Laboratory Association (NILA) and Partner at CRD Associates (Washington, DC).

Morton says NILA will continue to lobby for the broader PAMA reforms contained in the RESULTS Act. In particular, Morton says that there is concern that a minority of labs will report their private-payer payment data for 2025 to CMS by July 31, 2026. This could lead to a scenario similar to the first PAMA survey, which was  skewed toward pricing data submitted by the national labs. 
The result was three straight years (2018-2020) of 10% rate cuts to most test codes on the CLFS.

If passed, the RESULTS Act would remove the PAMA reporting burden from labs. Instead, pricing data would be supplied to CMS from an independent nonprofit entity (e.g., The FAIR Health
Database). This would ensure that pricing data from all labs (independents, hospitals and POLs) was accurately represented.

ACLA President Susan Van Meter says the next best chance for getting the RESULTS Act passed into law would be to have it inserted into a bigger budget bill expected to be introduced at the end of the year.

However, lab policy expert Dennis Weissman, says that passing the RESULTS Act into law will be difficult because it is likely to have a projected 10-year cost of billions of dollars. Furthermore, Weissman notes the new PAMA reporting period was only delayed by three months. Once the reporting process begins on May 1, it may be hard to stop, notes Weissman, who heads Dennis
Weissman & Associates (Falls Church, VA).

PAMA Policies included in Consolidated Appropriations Act of 2026 (Section 6226):

  • Delays PAMA rate cuts of up to 15% on about 800 tests and freezes the Clinical Laboratory Fee Schedule (CLFS) through December 31, 2026.
  • Updates private payer data CMS will use to set CLFS rates for 2027 by shifting the data collection period to January 1 – June 30, 2025 (previously it was January 1 – June 30, 2019).
  • Moving to an updated data collection period should allow for improved data reporting, as 2019 data was inaccessible to many laboratories.
  • CMS is preparing a laboratory data reporting educational campaign to inform hospital outreach, independent and physician office laboratories (POLs) of the requirement to report 2025 data.
  • Shifts the data reporting period to May 1, 2026 – July 31, 2026, after which CMS will calculate volume-weighted median private-payer rates to set CLFS rates effective January 1, 2027.

Which labs must report?
“Applicable laboratories” include those that bill Medicare Part B under their own National Provider Identifier (NPI) numbers. These include independent labs, hospital outreach labs and physician office labs that received at least $12,500 of Medicare revenues from the CLFS between January 1 and June 30, 2025. Hospital outreach labs must report if they bill Medicare Part B on Form CMS1450 under type of bill 14x. This means that approximately 3,000 hospitals with CLFS revenue are required to report.

Which data must be reported?
Applicable labs must report their private-payer payment data for nearly all test codes (~1,500 lab tests) on the CLFS to CMS beginning May 1, 2026, through July 31, 2026. The required data includes private-payer volume and rates from final claims paid between January 1 and June 30, 2025. CMS will use this information to calculate a volume-weighted median rate for each CPT code and to set new Medicare CLFS rates for 2027-2029. CLFS rates for 2027-2029 will be subject to a maximum annual cut of 15% per year.

What are the penalties for not reporting?
Failure to report could result in a penalty of up to $10,000 per day. After the first PAMA survey, CMS never set up a system for tracking non-reporting labs and instituting civil monetary policies. However, the agency’s leniency may not continue for the next PAMA reporting period. More information on PAMA reporting is available here.


Publicly Traded Lab Revenue Up 5% In First-Half 2024

Publicly Traded Lab Revenue Up 5% In First-Half 2024

Publicly Traded Lab Revenue Up 5% In First-Half 2024

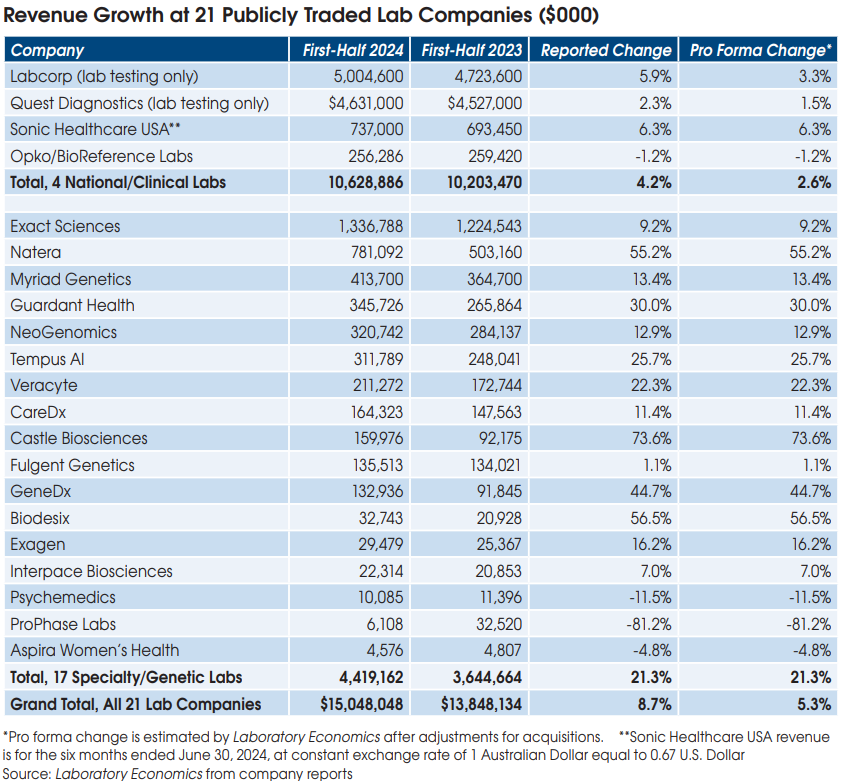
On a combined basis, 21 publicly traded labs reported revenue growth of 5% to reach $15 billion during the first six months of 2024 (after adjusting for acquisitions), according to financial reports collected by Laboratory Economics.

Among four national clinical labs (Quest Diagnostics, Labcorp, Sonic Healthcare USA and BioReference), combined revenue grew by 2.6% (after adjusting for acquisitions).

Meanwhile, among 17 specialty and genetic testing labs, combined pro-forma revenue increased by 21%.

Revenue growth was fastest at Castle Biosciences (Friendswood, TX), up 74% to $160 million. Castle’s lead product is its DecisionDx-Melanoma test for cutaneous melanoma (CPT 81529 at a Medicare rate of $7,193). Reported test results for DecisionDx-Melanoma increased by 11% to 17,969 tests in the six months ended June 30, 2024. Castle’s fastest-growing test was its TissueCypher Barrett’s Esophagus test (CPT 0108U at a Medicare rate of $4,950). Reported test result volume for TissueCypher was up 190% to 8,211 tests.

Next-Gen Sequencing Database

Next-Gen Sequencing Database

Next-Gen Sequencing Database

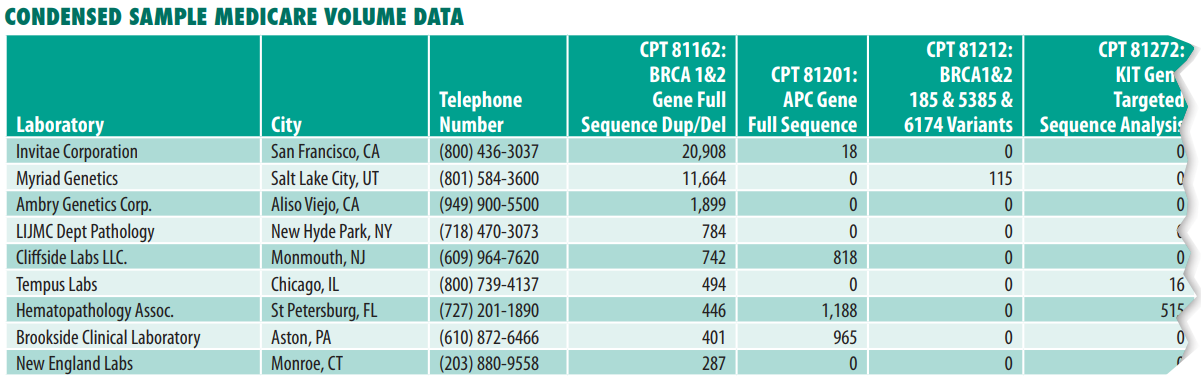
Laboratory Economics is offering a database of all 149 independent labs, 181 hospitals and 8 pathologists and other providers that perform Next-Gen Sequencing for 31 CPT and PLA procedure codes (e.g., 81432, 81433, 81435, 81437, 81450, etc.). The database includes annual Medicare Part B test volumes and allowed payments by test code for each provider (for calendar-year 2022). The database comes in easy-to-use and searchable Excel spreadsheets.

  • The data is in a user-friendly-excel spreadsheet that includes:
    • National Provider Identifier (NPI)
    • Provider Name & Complete Address + Phone
    • Specific Annual Medicare Part B Test Volume for 31 NGS CPT Codes for all Independent Labs, Hospitals,
    • Pathologists and Other Providers (2022)
    • Specific Annual Medicare Part B Allowed Payments for 31 NGS CPT Codes for all Independent Labs, Hospitals,
    • Pathologists and Other Providers (2022)
    • Overall Annual Next-Gen Sequencing Test Volume and Revenue Estimates for each Provider (2023)


  • Provide your sales rep with the data they need to succeed!
    • Data for all 50 states and Puerto Rico
    • Find NGS labs, hospitals and pathologists who can become your clients
    • Locate new NGS lab clients to grow your sales
    • Create targeted lists by location or specialty to focus on your best opportunities
    • Identify underserved markets for geographic expansion
    • Save time and money by using accurate, complete and consistent data

Is Alzheimer’s Testing the Next Big Lab Market?

Is Alzheimer’s Testing the Next Big Lab Market?

Is Alzheimer’s Testing the Next Big Lab Market?

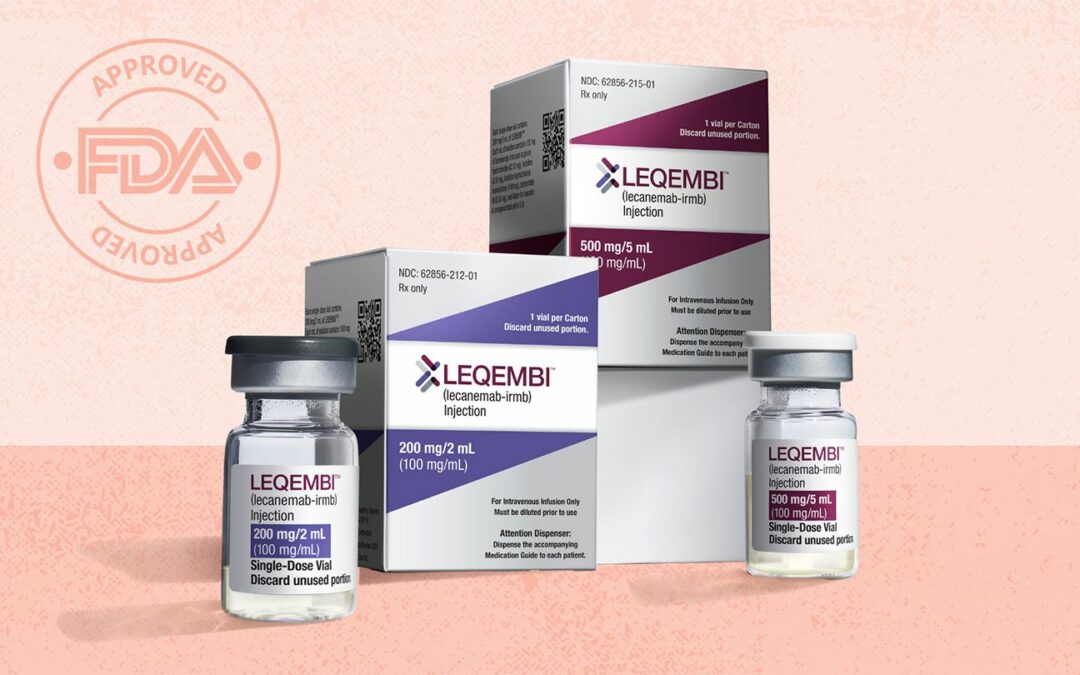
The FDA cleared the Alzheimer’s drug Leqembi (lecanemab) in July 2023. The drug marked the first treatment for slowing Alzheimer’s progression and cognitive decline to make it through the agency’s traditional pathway. But Leqembi, which was developed by Eisai (Tokyo) and Biogen (Cambridge, MA), has fallen far short of its goals for patient prescriptions. That’s partly because the current methods for diagnosing Alzheimer’s—ex- pensive brain imaging scans and invasive cerebral spinal fluid (CSF) tests— are acting as bottlenecks. However, new blood tests for Alzheimer’s are
being introduced that could give more patients access to treatment.

An estimated 6.9 million Americans aged 65 and older are currently living with Alzheimer’s disease, according to the Alzheimer’s Association (Chicago, IL). And an estimated 500,000 new cases of Alzheimer’s will be diagnosed this year. The new Alzheimer’s treatment Leqembi has a list price of $26,500 per year.

In addition, the FDA recently cleared Eli Lilly’s Alzheimer’s drug Kisunla (donanemab), which has a list price of $32,000 per year. Both drugs are intravenous infusions that attack a protein (amyloid) that clumps into plaques in the brains of people with Alzheimer’s. Both drugs slow disease progression (e.g., memory loss or other cognitive problems) but do not stop or reverse it. In addition, at least nine pharmaceutical companies have clinical trials underway for new Alzheimer’s drugs. Those in late-stage trials for oral pill treatments include BioVie (NE3107) and AB Science (masitinib).

But these drugs rely on PET scans and CSF tests to identify Alzheimer’s patients for treatment. “The availability of more affordable and minimally invasive diagnostic tools will help support broad access for the management of Alzheimer’s disease,” according to Eisai’s global Alzheimer’s disease officer, Keisuke Naito.

New blood-based immunoassays that identify the proteins associated with Alzheimer’s are likely to become the new standard for screening and monitoring the disease. The potential lab market could reach $500+ million per year. This estimate assumes 4 blood tests to identify and monitor each of the 500,000 new cases of Alzheimer’s each year at an average reimbursement of $260 per test (for two protein markers per test).

At the June 25th Annual CLFS Meeting with CMS to address rate setting for new codes, ACLA requested a Medicare rate of $130 per Alzheimer’s protein marker. Thus, a two-protein test (e.g., pTau181 & Abeta42) would be reimbursed $260. This level of reimbursement would match the Medicare rate of $260 for Fujirebio’s FDA-cleared Lumipulse test. Coding and final rates will be announced by CMS later this year for an effective date of January 1, 2025.

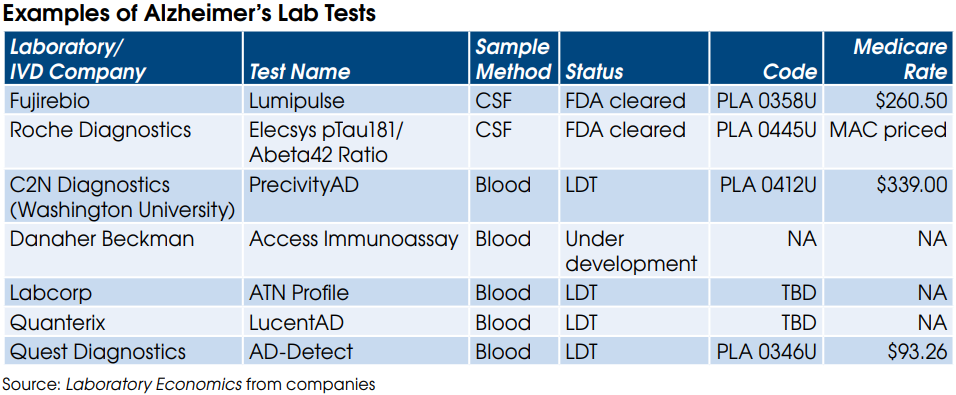
There are currently at least six Alzheimer’s lab tests on the market (see table). In addition, Danaher’s Beckman Coulter is developing a blood test for its immunoassay analyzers. Beckman is expected to release a two-protein test (pTau217 & Abeta42) in RUO format later this year. Clinical data from the RUO test will be used to support an eventual FDA application.