University Medical Center Getting New Lab in Southern Nevada

University Medical Center Getting New Lab in Southern Nevada

A new clinical lab being built by Nevada Health and Biosciences Laboratory in conjunction with University Medical Center of Southern Nevada (UMC) is expected to open in early 2027. The 34,000-square-foot lab will initially employ about 35 people and will significantly expand UMC’s current test offerings. Laboratory Economics recently spoke with Deb LaCava, Administrative Director of Laboratory Services at UMC.

Tell me about the new Nevada Health and Biosciences Academic Laboratory.
It’s located in the Las Vegas Medical District and will significantly expand UMC’s capacity while supporting education, research and future transplant-related services. When we first open, we will be moving our molecular and microbiology labs from the main hospitals into that building and expanding both. We’re having a BSL-3 lab built into that facility, so that will expand our capacity in microbiology. We’ll also be bringing in toxicology and drug testing. We’ll have mass spec, and we also are planning an HLA lab for transplants.
What was the impetus for the new lab?
Medical care is lacking in Nevada compared to our neighboring states. A lot of patient testing must be sent out of state to reference labs, and that really delays patient care. Our new lab will get results to patients in a couple of hours instead of seven or eight days.
Where is the majority of testing done now?
Routine testing is generally performed in the hospital lab. More specialized tests, such as NGS or specialized panels, are sent out to a reference lab such as Labcorp or Quest.
What geographic areas will the new lab serve?
Initially, it will serve the Las Vegas Valley. I’ve had calls from Arizona and California labs asking us to do testing for them, so once we’re set up and ready, we’ll expand our range. Some of it has to do with licensing. Not every state requires a license, but California does.
How many clients are you currently serving, and do you expect that to increase with the new lab?
Outside of the UMC hospitals, we have about 14 reference clients that send us testing on an almost daily basis. It accounts for about $1 million of testing per year. I anticipate getting more clients once the new lab is open. We anticipate increasing the testing for our UMC patients as well, as they represent the biggest client population for the lab.
Do you expect your volume to increase substantially?
Right now, our lab runs about 7.5 million tests per year—mostly inpatient testing. Between molecular and microbiology, we run just under 2 million tests per year. We’re hoping to initially add at least another 500,000 in that first year. I anticipate adding volume each year for the first three or four years.
How will the new lab improve turnaround times?
Right now, specialized testing is sent to a reference lab. Most of them are out of state, such as California, Arizona and the East Coast. This causes delays just for transit times. And because of batch testing, some of the labs may only perform a test two or three days per week. So right now, any testing that’s sent out of state is averaging five to 10 days turnaround time. If we do the testing here, we can give the physicians 24-hour maximum turnaround time with most test results reported in four to six hours.
What else will the new lab offer?
We’ll have a BSL-3 lab. We are already the designated hospital if there’s an Ebola case here in town. We’ll also be able to do tuberculosis confirmation and some other tests, such as Zika. The big part of this will be the HLA lab. Once that opens, we’ll be supporting our own transplant program. We’ll also be able to support platelet matching for patients who need blood transfusions and surgeries.
How will this lab affect workforce development in Southern Nevada?
We plan on adding several full-time employees when the lab first opens, and as we grow, we’ll likely add more. I think the biggest contribution to the workforce will be the training we’ll be able to provide for future lab professionals. They’ll be able to have hands-on experience in a state-of-the-art lab.

How many med tech students are you training right now?
We generally have four rotating through our labs at any given time. We train them for eight weeks. With the added space and staff in the new lab, we’ll be able to train 2-4 more per year.

Tempus AI at the Top of America’s Fastest Growing Labs

Tempus AI at the Top of America’s Fastest Growing Labs

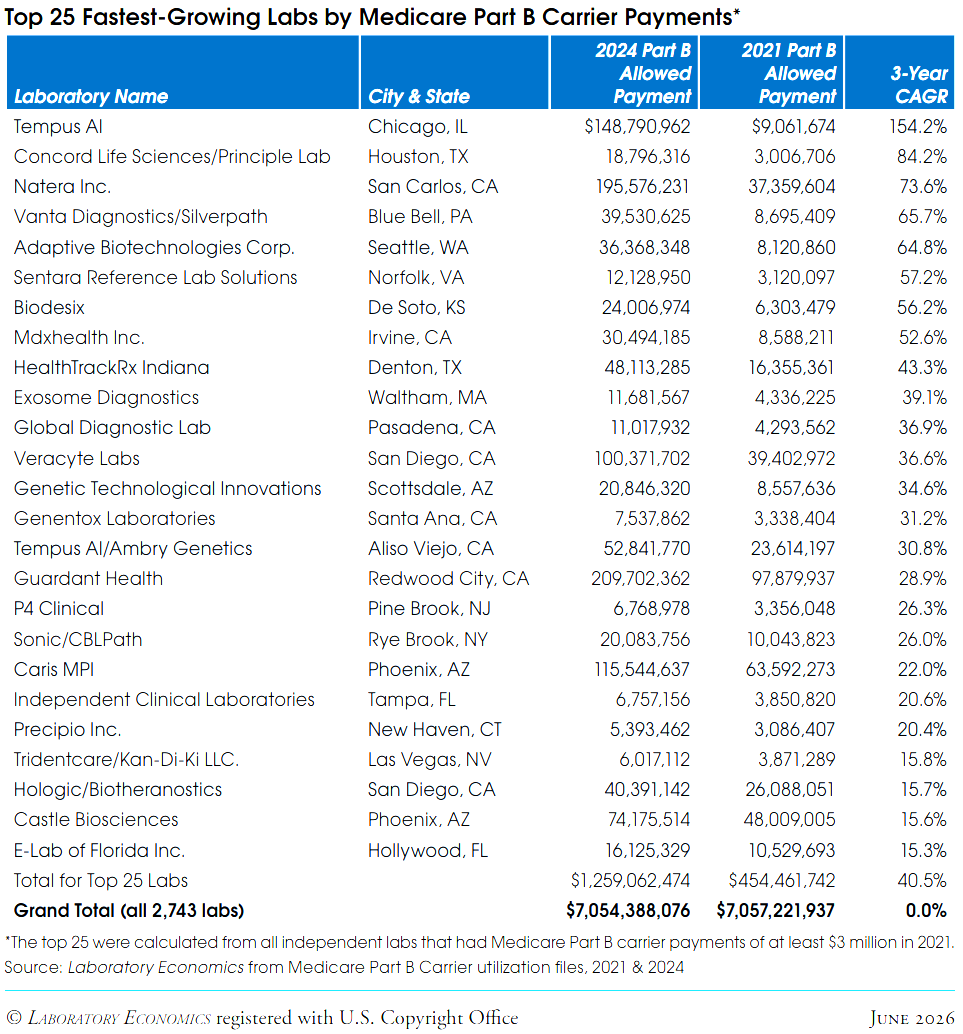
Tempus AI (Chicago, IL) was the fastest growing lab from 2021-2024 based on the newly released Medicare Part B payment data for 2024. Tempus AI’s Medicare Part B allowed payments jumped from $9.1 million in 2021 to $148.8 million in 2024 for a compound annual growth rate (CAGR) of 154%. Tempus AI, which had an IPO in June 2024, specializes in next-gen sequencing and PCR-based testing.

Concord Life Sciences (Houston, TX) received $18.8 million in Part B allowed payments in 2024, an increase of 84% per year from $3 million in 2021. Concord (dba Principle Laboratory) specializes in nursing home lab services and PCR testing.

Natera Inc. (San Carlos, CA) received $195.6 million from Medicare Part B allowed payments in 2024, an increase of 74% per year from $37.4 million in 2021. Natera specializes in minimal residual disease (MRD) testing for cancer patients.

PAMA Delay Included in New Spending Law

PAMA Delay Included in New Spending Law

PAMA Delay Included in New Spending Law

On Feb. 3, President Trump signed into law a $1.2 trillion spending
package. Included in the Consolidated Appropriations Act of 2026 is a freeze in Medicare CLFS rates through December 31, 2026. In addition, the new law modifies the private-payer data collection and reporting period for labs. Labs will now have to collect their private-payer payment data from January 1 – June 30, 2025, and report it to CMS between May 1, 2026 – July 31, 2026. CMS will use this data to calculate CLFS rates for 2027. “This is welcome relief, but what we really need is permanent reform,” says Erin Morton, Washington Representative for the National Independent Laboratory Association (NILA) and Partner at CRD Associates (Washington, DC).

Morton says NILA will continue to lobby for the broader PAMA reforms contained in the RESULTS Act. In particular, Morton says that there is concern that a minority of labs will report their private-payer payment data for 2025 to CMS by July 31, 2026. This could lead to a scenario similar to the first PAMA survey, which was  skewed toward pricing data submitted by the national labs. 
The result was three straight years (2018-2020) of 10% rate cuts to most test codes on the CLFS.

If passed, the RESULTS Act would remove the PAMA reporting burden from labs. Instead, pricing data would be supplied to CMS from an independent nonprofit entity (e.g., The FAIR Health
Database). This would ensure that pricing data from all labs (independents, hospitals and POLs) was accurately represented.

ACLA President Susan Van Meter says the next best chance for getting the RESULTS Act passed into law would be to have it inserted into a bigger budget bill expected to be introduced at the end of the year.

However, lab policy expert Dennis Weissman, says that passing the RESULTS Act into law will be difficult because it is likely to have a projected 10-year cost of billions of dollars. Furthermore, Weissman notes the new PAMA reporting period was only delayed by three months. Once the reporting process begins on May 1, it may be hard to stop, notes Weissman, who heads Dennis
Weissman & Associates (Falls Church, VA).

PAMA Policies included in Consolidated Appropriations Act of 2026 (Section 6226):

  • Delays PAMA rate cuts of up to 15% on about 800 tests and freezes the Clinical Laboratory Fee Schedule (CLFS) through December 31, 2026.
  • Updates private payer data CMS will use to set CLFS rates for 2027 by shifting the data collection period to January 1 – June 30, 2025 (previously it was January 1 – June 30, 2019).
  • Moving to an updated data collection period should allow for improved data reporting, as 2019 data was inaccessible to many laboratories.
  • CMS is preparing a laboratory data reporting educational campaign to inform hospital outreach, independent and physician office laboratories (POLs) of the requirement to report 2025 data.
  • Shifts the data reporting period to May 1, 2026 – July 31, 2026, after which CMS will calculate volume-weighted median private-payer rates to set CLFS rates effective January 1, 2027.

Which labs must report?
“Applicable laboratories” include those that bill Medicare Part B under their own National Provider Identifier (NPI) numbers. These include independent labs, hospital outreach labs and physician office labs that received at least $12,500 of Medicare revenues from the CLFS between January 1 and June 30, 2025. Hospital outreach labs must report if they bill Medicare Part B on Form CMS1450 under type of bill 14x. This means that approximately 3,000 hospitals with CLFS revenue are required to report.

Which data must be reported?
Applicable labs must report their private-payer payment data for nearly all test codes (~1,500 lab tests) on the CLFS to CMS beginning May 1, 2026, through July 31, 2026. The required data includes private-payer volume and rates from final claims paid between January 1 and June 30, 2025. CMS will use this information to calculate a volume-weighted median rate for each CPT code and to set new Medicare CLFS rates for 2027-2029. CLFS rates for 2027-2029 will be subject to a maximum annual cut of 15% per year.

What are the penalties for not reporting?
Failure to report could result in a penalty of up to $10,000 per day. After the first PAMA survey, CMS never set up a system for tracking non-reporting labs and instituting civil monetary policies. However, the agency’s leniency may not continue for the next PAMA reporting period. More information on PAMA reporting is available here.

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

Laboratory Economics has just released The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028. With this special report, you can tap into 100+ pages of proprietary market research that reveals critical data and information about key business trends affecting the anatomic pathology market.

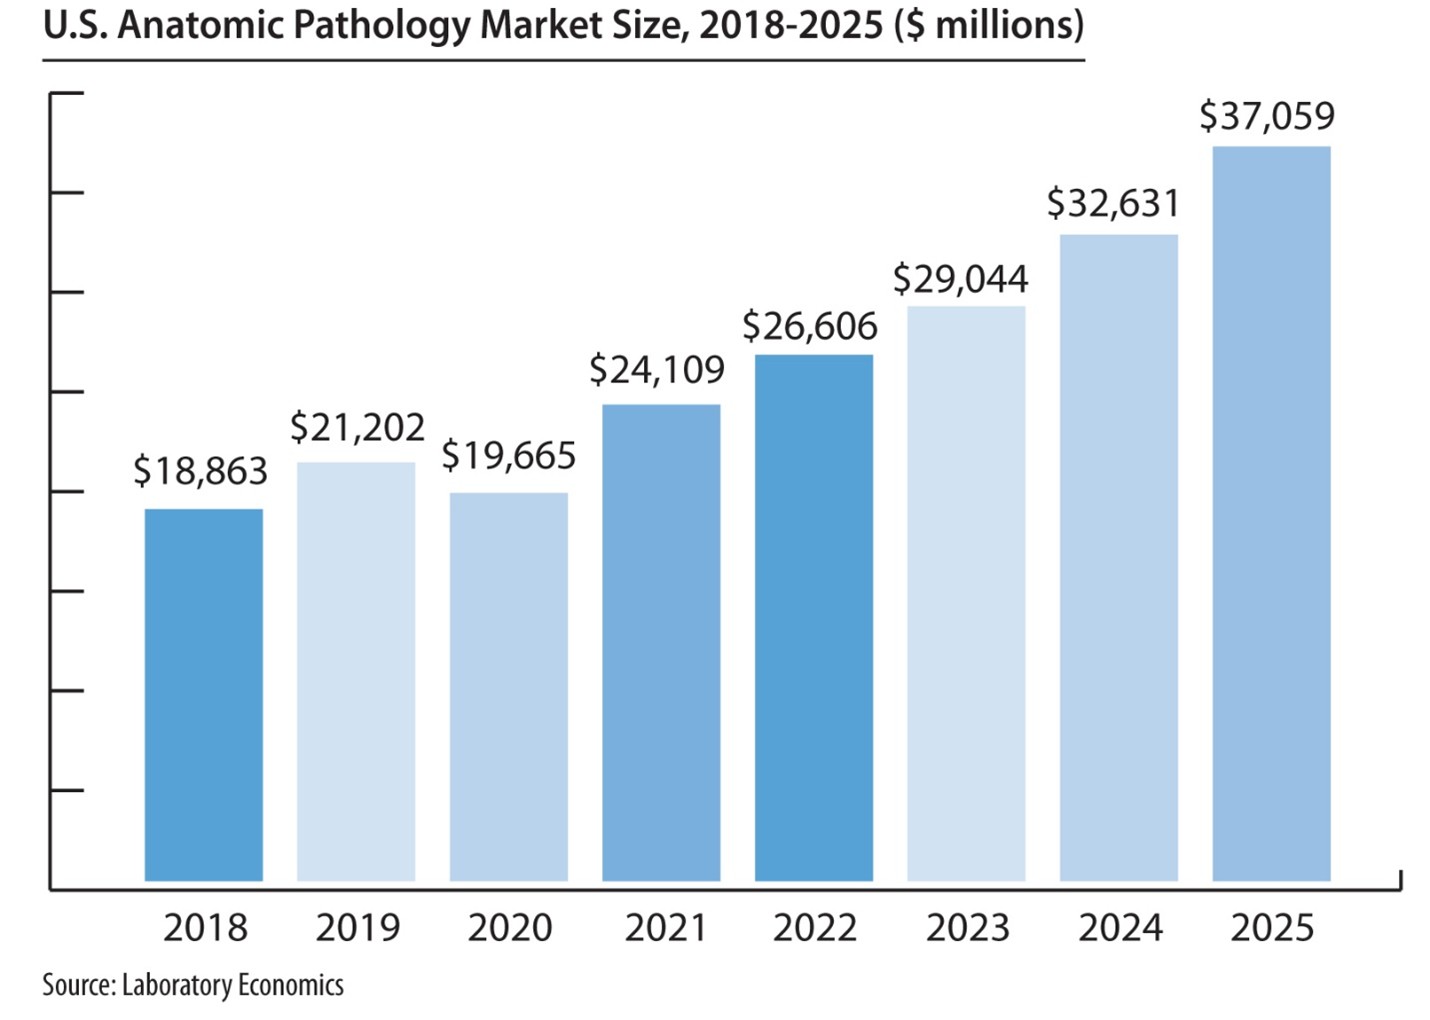
The report reveals that the U.S. anatomic pathology market represented an estimated $37.1 billion of revenue in 2025 with a long-term annual growth rate of 10.1%. Growth is being driven almost entirely by increased molecular oncology testing, especially minimal residual disease (MRD) testing to monitor cancer treatment.

The U.S. anatomic pathology market faces unprecedented change, including the introduction of artificial intelligence tools that increase pathologist productivity, greater utilization management by private payers and persistent reimbursement pressure.


“The introduction of new higher-priced molecular oncology tests, including next-generation sequencing for tumor mutation profiling and MRD testing, should more than offset price and volume pressure on routine pathology tests,” according to Jondavid Klipp, President of Laboratory Economics.

In addition, the growing adoption of digital pathology and application of AI software tools to digitized slide images have the potential to profoundly change the way pathology is practiced within the next 3-5 years.

The greatest challenge comes from third-party payers, which are instituting prior authorization policies and laboratory benefit management programs designed to lower utilization of anatomic pathology services and genetic tests for cancer.

The report includes:

  • More than 100 charts and graphs
  • Pathology market size and growth rates
  • Detailed estimates for market subsets like uropathology, dermatopathology, and gastrointestinal pathology
  • In-depth analysis of the molecular oncology testing market size and growth rates
  • Medicare claims data for 60+ key pathology codes covering surgical pathology, molecular oncology, immunohistochemistry and special stains, tumor marker immunoassays, FISH testing and flow cytometry
  • Cervical cancer testing trends and pricing data
  • Detailed analysis of the emerging digital pathology & AI market
  • Results from Laboratory Economics Anatomic Pathology and Clinical Lab Trends Surveys from 2015 through 2025

Anatomic pathology companies highlighted include:

  • Adaptive Biotechnologies
  • Bako Diagnostics
  • Caris Life Sciences
  • CellNetix Pathology & Laboratories
  • Exact Sciences
  • Foundation Medicine
  • Fulgent Genetics/Inform Diagnostics
  • Guardant Health
  • Labcorp
  • Mayo Clinic Laboratories
  • Myriad Genetics
  • Natera Inc.
  • NeoGenomics
  • OPKO/BioReference Labs
  • PathGroup
  • Quest Diagnostics
  • Sonic Healthcare/Aurora Diagnostics/ProPath Services
  • Tempus AI
  • Versant Diagnostics

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028 is published by Laboratory Economics (http://www.laboratoryeconomics.com), an independent market research firm focused exclusively on the business of pathology and laboratory medicine. Report author Jondavid Klipp has been covering key business trends affecting clinical lab testing and anatomic pathology services for 27 years.


New PAMA Reform Bill Would Freeze CLFS Rates Through 2028

New PAMA Reform Bill Would Freeze CLFS Rates Through 2028

New PAMA Reform Bill Would Freeze CLFS Rates Through 2028

A bipartisan bill that would freeze Medicare Clinical Lab Fee Schedule (CLFS) rates for 2026-2028 and overhaul the way that future CLFS rates are determined was introduced on September 10.

The Reforming and Enhancing Sustainable Updates to Laboratory Testing Services (RESULTS) Act was proposed by Reps. Richard Hudson (R-NC), Gus Bilirakis (R-FL), Brian Fitzpatrick (R-PA) and Scott Peters (D-CA) in the House of Representatives. A Senate version has been introduced by
Sens. Thom Tillis (R-NC) and Raphael Warnock (D-GA).

ACLA President Susan Van Meter says it’s now critical for the entire lab industry to show support for the RESULTS Act by contacting members of the Senate Finance, House Ways & Means and especially the House Energy & Commerce committees. The goal is to get the RESULTS Act inserted
into a broader healthcare package expected to be passed later this year.

ACLA has not finalized its estimate of what it thinks the RESULTS Act might cost. A critical factor to gaining passage is Congressional Budget Office (CBO) scoring. The understaffed CBO will need to be convinced that the RESULTS Act has a reasonable chance of passage before it devotes the time and resources to analyze its cost. A high-cost estimate from the CBO could doom passage into law. 

Without new legislation, Medicare CLFS rate cuts of up to 15% for roughly 800 lab tests will take effect on January 1, 2026. In addition, independent labs, hospital outreach labs and large POLs will be required to report their private-payer volume and payment data from 2019 for approximately 1,500 lab test codes by March 31, 2026. CMS will use this data to determine Medicare CLFS rates for 2027-2029.

The RESULTS Act would:

  • Freeze Medicare CLFS rates at current levels for 2026-2028.
  • Medicare CLFS rates for 2029-2032 would be based on weighted median private payer rates from January 1 – June 30, 2027.
  • Labs would no longer be required to report their private-payer payment data.
  • Data would be supplied to CMS from a claims database (including at least 50 billion lab claims from >50 private payers) from an independent nonprofit entity (e.g., The FAIR Health Database).
  • Rate cuts would be limited to 5% per year with no cap on rate increases.
  • Private-payer payment data would be collected and analyzed every 4 years (instead of 3 years).
  • Special reporting rules would apply to non-widely available lab test codes
    (100 or fewer labs perform) and for Advanced Diagnostic Lab Tests (ADLTs)

ACLA’s Van Meter says that the RESULTS Act removes the reporting burden from labs and would help ensure that all lag segments are accurately represented [especially highly reimbursed hospital outreach labs]. Lobbying efforts are being focused on committee members (Senate Finance and House Ways & Means and Energy & Commerce) because their support is necessary to advance the bill.

Previous efforts at PAMA reform, including the LAB Act (introduced 2019) and SALSA (introduced 2022), were unsuccessful primarily because of their estimated costs. For example, the CBO had estimated that passing SALSA into law would cost $6 billion over 10 years.

Over the past five years (2021-2025), Medicare CLFS rates have been frozen because of a series of one-year delays. Previously, the CBO had scored one-year delays to save money under the erroneous assumption that private payer lab test rates were increasing in line with inflation. However, the CBO is updating its forecasting model for the CLFS and another one-year freeze is unlikely.

The Outlook for Medicare CLFS Rates

The Outlook for Medicare CLFS Rates

The Outlook for Medicare CLFS Rates

Without legislative action, Medicare rates for nearly 800 lab tests 
will be cut by up to 15% effective January 1, 2026. “A lot of labs 
have become complacent after five straight years of Medicare CLFS rate 
freezes,” says Mark Birenbaum, PhD, Executive Director of the National  Independent Lab Association (St. Louis, MO). “But they need to start  thinking about the potential for rate cuts next year.”

Birenbaum says that NILA is working with the American Clinical Laboratory  Assn. to introduce a new “PAMA-fix” bill within the next month or two. Any new bill would seek to delay the scheduled Medicare CLFS rate cuts for  2026 and ensure that hospital lab rates are correctly represented 
in future private-payer payments surveys and rate calculations. 
It’s too late to get a PAMA-fix into the Big Beautiful Bill currently being  debated in the Senate. 

The hope is that a PAMA-fix could get inserted into a major government  funding or healthcare policy bill at the end of the year. But this will be a  tough hill to climb, and time is running short. 

Here’s an outline of three possible scenarios: 

Scenario 1: PAMA Proceeds as Scheduled by Law
The first PAMA survey, which was based on private-payer lab rates from  2016, resulted in three straight years (2018-2020) of 10% cuts to most lab  tests on the Medicare CLFS. A second PAMA survey and additional rate cuts  were then frozen for five straight years (2021-2025). 

Under current law, Medicare CLFS rates for approximately 800 lab tests will be reduced by up to 15% on January 1, 2026. See table on page 4. 

In addition, the second PAMA survey is scheduled to begin on January 1,  2026. Independent labs, hospitals and large POLs are required to submit  their private-payer volumes and reimbursement rates from the period  January 1, 2019 to June 30, 2019 to CMS by March 31, 2026. CMS will use 
this data to calculate new median private-payer rates to set the Medicare CLFS for 2027-2029.

Scenario 2: A PAMA-Fix is Introduced and Passed into Law
Despite widespread support from both Democrats and Republicans, the  last PAMA-fix bill SALSA (H.R. 2377/S. 1000) failed to get passed into law. The  culprit was cost. The Congressional Budget Office (CBO) had projected that  passing SALSA into law would cost $6 billion over 10 years. A separate  analysis by ACLA had estimated the cost at less than $3 billion. 

ACLA is now crafting a new PAMA-fix proposal and seeking supporters to  introduce it. A simpler and less costly alternative to SALSA is what’s needed. 

There is little argument that current PAMA law pertaining to labs is  unworkable. In particular, it will be nearly impossible for most hospital labs  to dig up their private-payer volume and payment data from 2019 and  report it to CMS, notes Josh Kramer, Managing Partner at the laboratory IT  company Leap Consulting Group (Teaneck, NJ). Kramer says that many  hospitals have gone through system upgrades and changes since 2019 and these hospitals may not have historical claims data readily available from  legacy systems. In addition, PAMA does not allow hospitals to ignore paper  claims data. And smaller hospitals may not have detailed lab data from  paper claims loaded in their systems at all, according to Kramer. 

A new PAMA-fix bill will need to include a mechanism (e.g., statistical  sampling) to ensure that the higher rates paid to hospital labs are  accurately surveyed and included in CLFS rate calculations. 

Scenario 3: CLFS Remains Frozen and PAMA is Delayed Another Year
In previous scoring of one-year delays in PAMA payment cuts and reporting, the CBO assumed that private payers were adjusting their lab test reimbursement rates for inflation. Based on this assumption, the CBOconcluded that the suspension of PAMAwould result in cost savings.  The CBO is no longer assuming private payer inflation updates. As a result,  another one-year PAMA delay is unlikely to be scored to provide savings and  thus unlikely to be passed into law.