University Medical Center Getting New Lab in Southern Nevada

University Medical Center Getting New Lab in Southern Nevada

A new clinical lab being built by Nevada Health and Biosciences Laboratory in conjunction with University Medical Center of Southern Nevada (UMC) is expected to open in early 2027. The 34,000-square-foot lab will initially employ about 35 people and will significantly expand UMC’s current test offerings. Laboratory Economics recently spoke with Deb LaCava, Administrative Director of Laboratory Services at UMC.

Tell me about the new Nevada Health and Biosciences Academic Laboratory.
It’s located in the Las Vegas Medical District and will significantly expand UMC’s capacity while supporting education, research and future transplant-related services. When we first open, we will be moving our molecular and microbiology labs from the main hospitals into that building and expanding both. We’re having a BSL-3 lab built into that facility, so that will expand our capacity in microbiology. We’ll also be bringing in toxicology and drug testing. We’ll have mass spec, and we also are planning an HLA lab for transplants.
What was the impetus for the new lab?
Medical care is lacking in Nevada compared to our neighboring states. A lot of patient testing must be sent out of state to reference labs, and that really delays patient care. Our new lab will get results to patients in a couple of hours instead of seven or eight days.
Where is the majority of testing done now?
Routine testing is generally performed in the hospital lab. More specialized tests, such as NGS or specialized panels, are sent out to a reference lab such as Labcorp or Quest.
What geographic areas will the new lab serve?
Initially, it will serve the Las Vegas Valley. I’ve had calls from Arizona and California labs asking us to do testing for them, so once we’re set up and ready, we’ll expand our range. Some of it has to do with licensing. Not every state requires a license, but California does.
How many clients are you currently serving, and do you expect that to increase with the new lab?
Outside of the UMC hospitals, we have about 14 reference clients that send us testing on an almost daily basis. It accounts for about $1 million of testing per year. I anticipate getting more clients once the new lab is open. We anticipate increasing the testing for our UMC patients as well, as they represent the biggest client population for the lab.
Do you expect your volume to increase substantially?
Right now, our lab runs about 7.5 million tests per year—mostly inpatient testing. Between molecular and microbiology, we run just under 2 million tests per year. We’re hoping to initially add at least another 500,000 in that first year. I anticipate adding volume each year for the first three or four years.
How will the new lab improve turnaround times?
Right now, specialized testing is sent to a reference lab. Most of them are out of state, such as California, Arizona and the East Coast. This causes delays just for transit times. And because of batch testing, some of the labs may only perform a test two or three days per week. So right now, any testing that’s sent out of state is averaging five to 10 days turnaround time. If we do the testing here, we can give the physicians 24-hour maximum turnaround time with most test results reported in four to six hours.
What else will the new lab offer?
We’ll have a BSL-3 lab. We are already the designated hospital if there’s an Ebola case here in town. We’ll also be able to do tuberculosis confirmation and some other tests, such as Zika. The big part of this will be the HLA lab. Once that opens, we’ll be supporting our own transplant program. We’ll also be able to support platelet matching for patients who need blood transfusions and surgeries.
How will this lab affect workforce development in Southern Nevada?
We plan on adding several full-time employees when the lab first opens, and as we grow, we’ll likely add more. I think the biggest contribution to the workforce will be the training we’ll be able to provide for future lab professionals. They’ll be able to have hands-on experience in a state-of-the-art lab.

How many med tech students are you training right now?
We generally have four rotating through our labs at any given time. We train them for eight weeks. With the added space and staff in the new lab, we’ll be able to train 2-4 more per year.


University Medical Center Getting New Lab in Southern Nevada

Dallas Lab to Pay $24 Million for Alleged Covid-19 Testing Fraud

Magnolia Diagnostics (Dallas, TX) and its owners and investors have agreed to pay $24 million to resolve allegations that the lab billed Medicare for unnecessary respiratory tests for seniors during the pandemic.

The U.S. Department of Justice alleges that, beginning in April 2020, owners John Bains and Kelly Bains, acting through Magnolia, required senior living communities seeking Covid-19 testing to also obtain expensive respiratory pathogen panels (RPPs).

To implement this strategy, Magnolia used prepopulated requisition forms that selected RPP testing and associated diagnosis codes before any individualized clinical assessment occurred. Magnolia allegedly treated provider signatures on those forms as blanket or standing orders authorizing RPPs for all seniors across entire communities or chains of communities, and then used those purported authorizations to perform RPPs on specimens collected during community-wide Covid-19 testing. At times, John Bains allegedly threatened to withhold Covid-19 testing from communities that asked not to receive RPPs.

Furthermore, Magnolia allegedly froze and stored thousands of respiratory specimens, sometimes for weeks or months, before thawing and testing them. Magnolia thereby billed Medicare for useless test results, according to the DOJ.

During the three-year period from 2020-2022, Magnolia received Medicare Part B payments totaling more than $50 million. The Magnolia laboratory remains in business and now specializes in a wide variety of PCR testing. Ex-CEO John Bains now heads up a real estate development firm named Mountain Town Development.

New Bill Would Expand Price Transparency Requirements to Independent Labs

New Bill Would Expand Price Transparency Requirements to Independent Labs

The Patients Deserve Price Tags Act would significantly impact independent labs by bringing them under the same strict federal price transparency mandates that currently apply only to hospitals. Versions of the bill were introduced late last year in the Senate (S. 2355) and House (H.R. 5582). The bill would require independent labs to make monthly public disclosures of their negotiated reimbursement rates across their entire test menu. “The reporting requirements in the current draft are staggering,” stated the American Clinical Laboratory Association (ACLA) in a July 2 letter to Senate leaders.

New Bill Would Expand Price Transparency (cont’d from page 1) The champions behind the bipartisan Patients Deserve Price Tags Act are U.S. Senators Roger Marshall (R-KS) and John Hickenlooper (D-CO). So far, the proposed legislation has the support of a total of 24 Senators and 12 members of the House.

“Customers don’t walk into a restaurant only to find out how much the food costs when they get the bill. Patients should know the price of the service they need before they make any decisions,” according to Senator Marshall.

“We deserve to know exactly what we are paying for whether it’s a lab test, a colonoscopy, or an
MRI,” stated Senator Hickenlooper.

The Senate Committee on Health, Education, Labor, and Pensions (HELP) held a full committee hearing on the bill on March 19, 2026. In addition, the House Energy and Commerce Health Subcommittee held a hearing on June 10, 2026.

Effective July 1, 2027, the bill would require the following disclosures from all CLIA-certified clinical and anatomic pathology labs:

  • Public Rate Sheets: Labs must make publicly available, and update monthly, all negotiated rates with health insurance plans for all lab tests and ancillary services they offer.
  • Cash Discounts: Labs must explicitly disclose their standard discounted cash prices for patients paying out-of-pocket.
  • Standardized Descriptions: Lab tests must be listed with plain-language descriptions and standard billing codes so consumers can easily compare prices across different facilities.

Furthermore, labs that fail to post their rates or try to hide fees will face heavy financial penalties and enforcement actions under the proposed legislation. Labs that fail to comply are subject to a civil monetary penalty (CMP) of up to $300 per day. And the bill gives the U.S. Secretary of Health and Human Services (currently Robert F. Kennedy Jr.) the authority to increase the penalty starting in 2028.

In the letter to Senate leaders, ACLA President Susan Van Meter noted that there are more than 2,100 test codes on the Medicare Clinical Laboratory Fee Schedule alone and that some ACLA member labs have contracts with up to 900 health plans. Thus, the bill would require some large labs to review and post nearly two million rates each month (i.e., 2,100 codes x 900 plans). The reporting costs to meet this obligation would be significant and divert resources away from patient care, according to Van Meter.

“A far more reasonable approach—and one that would yield information that is truly useful to patients—would be to require clinical labs to post cash prices for those testing services on the CMS list of shoppable services,” according to Van Meter. There are currently 14 routine clinical lab tests specified in the CMS core list of 70 mandatory shoppable services.

Hospital Price Transparency

The Patients Deserve Price Tags Act also seeks to expand existing transparency requirements for hospitals. For example, the bill requires hospitals to update and post publicly their rates each month, rather than the current requirement of once a year. In addition, the bill dramatically increases penalties and mandates CMPs for every violation, removing CMS discretion. Under the

bill, for example, hospitals with more than 500 beds, would be subject to a $25 per bed per day fine (i.e., $12,500+ per day) for noncompliance.

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028

Laboratory Economics has just released The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028. With this special report, you can tap into 100+ pages of proprietary market research that reveals critical data and information about key business trends affecting the anatomic pathology market.

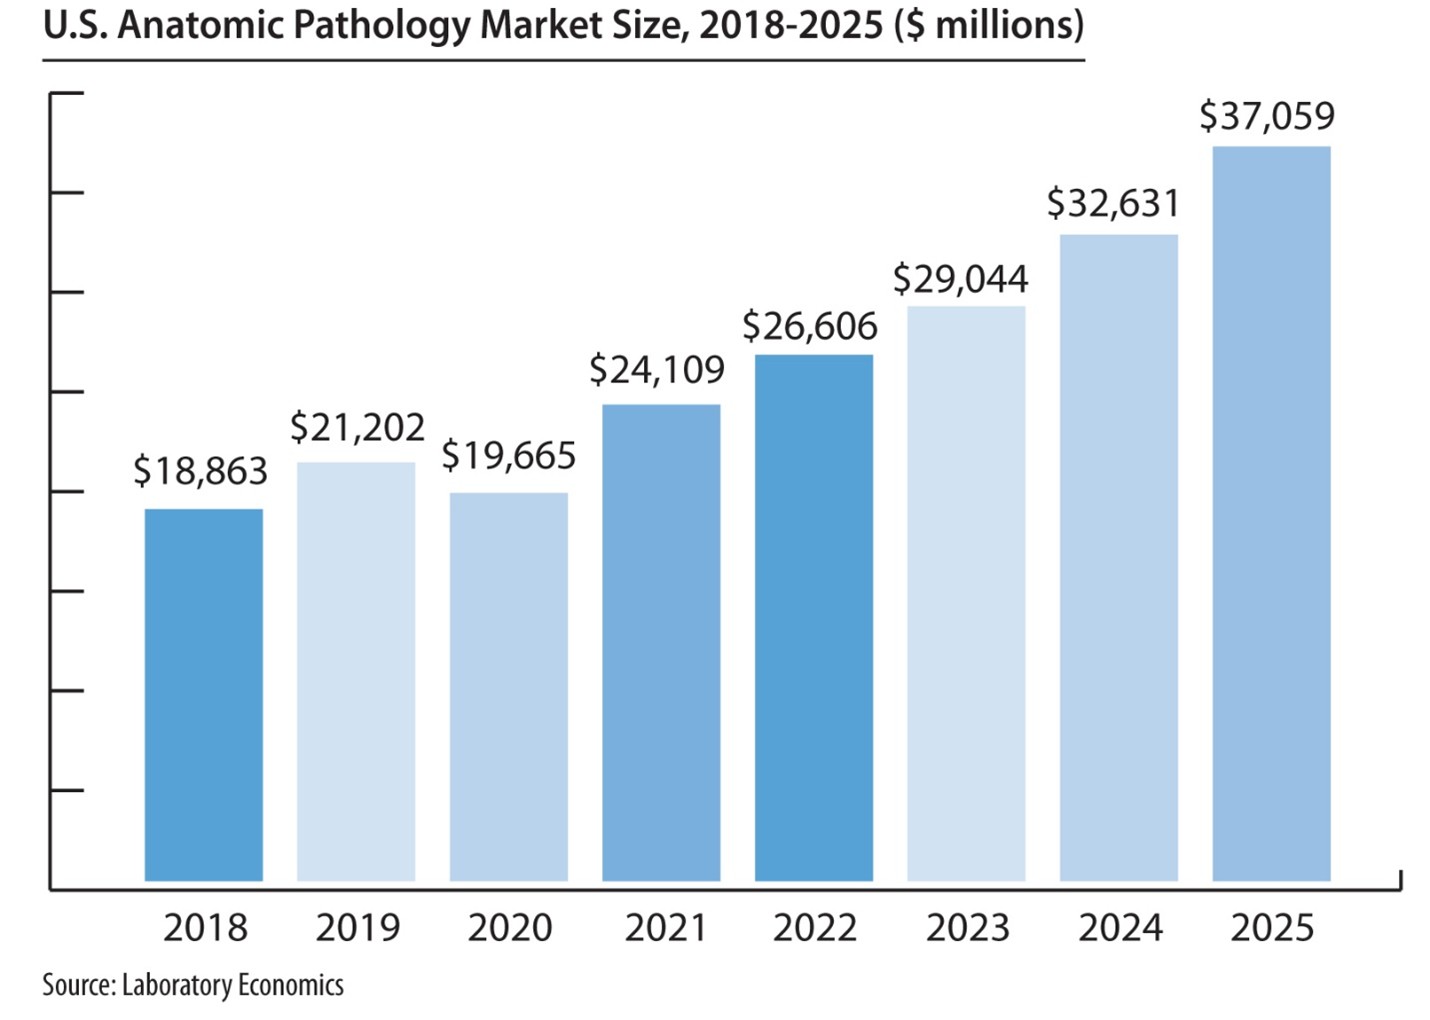
The report reveals that the U.S. anatomic pathology market represented an estimated $37.1 billion of revenue in 2025 with a long-term annual growth rate of 10.1%. Growth is being driven almost entirely by increased molecular oncology testing, especially minimal residual disease (MRD) testing to monitor cancer treatment.

The U.S. anatomic pathology market faces unprecedented change, including the introduction of artificial intelligence tools that increase pathologist productivity, greater utilization management by private payers and persistent reimbursement pressure.


“The introduction of new higher-priced molecular oncology tests, including next-generation sequencing for tumor mutation profiling and MRD testing, should more than offset price and volume pressure on routine pathology tests,” according to Jondavid Klipp, President of Laboratory Economics.

In addition, the growing adoption of digital pathology and application of AI software tools to digitized slide images have the potential to profoundly change the way pathology is practiced within the next 3-5 years.

The greatest challenge comes from third-party payers, which are instituting prior authorization policies and laboratory benefit management programs designed to lower utilization of anatomic pathology services and genetic tests for cancer.

The report includes:

  • More than 100 charts and graphs
  • Pathology market size and growth rates
  • Detailed estimates for market subsets like uropathology, dermatopathology, and gastrointestinal pathology
  • In-depth analysis of the molecular oncology testing market size and growth rates
  • Medicare claims data for 60+ key pathology codes covering surgical pathology, molecular oncology, immunohistochemistry and special stains, tumor marker immunoassays, FISH testing and flow cytometry
  • Cervical cancer testing trends and pricing data
  • Detailed analysis of the emerging digital pathology & AI market
  • Results from Laboratory Economics Anatomic Pathology and Clinical Lab Trends Surveys from 2015 through 2025

Anatomic pathology companies highlighted include:

  • Adaptive Biotechnologies
  • Bako Diagnostics
  • Caris Life Sciences
  • CellNetix Pathology & Laboratories
  • Exact Sciences
  • Foundation Medicine
  • Fulgent Genetics/Inform Diagnostics
  • Guardant Health
  • Labcorp
  • Mayo Clinic Laboratories
  • Myriad Genetics
  • Natera Inc.
  • NeoGenomics
  • OPKO/BioReference Labs
  • PathGroup
  • Quest Diagnostics
  • Sonic Healthcare/Aurora Diagnostics/ProPath Services
  • Tempus AI
  • Versant Diagnostics

The U.S. Anatomic Pathology Market: Forecast & Trends 2025-2028 is published by Laboratory Economics (http://www.laboratoryeconomics.com), an independent market research firm focused exclusively on the business of pathology and laboratory medicine. Report author Jondavid Klipp has been covering key business trends affecting clinical lab testing and anatomic pathology services for 27 years.


New Bill Would Expand Price Transparency Requirements to Independent Labs

New PAMA Reform Bill Would Freeze CLFS Rates Through 2028

New PAMA Reform Bill Would Freeze CLFS Rates Through 2028

A bipartisan bill that would freeze Medicare Clinical Lab Fee Schedule (CLFS) rates for 2026-2028 and overhaul the way that future CLFS rates are determined was introduced on September 10.

The Reforming and Enhancing Sustainable Updates to Laboratory Testing Services (RESULTS) Act was proposed by Reps. Richard Hudson (R-NC), Gus Bilirakis (R-FL), Brian Fitzpatrick (R-PA) and Scott Peters (D-CA) in the House of Representatives. A Senate version has been introduced by
Sens. Thom Tillis (R-NC) and Raphael Warnock (D-GA).

ACLA President Susan Van Meter says it’s now critical for the entire lab industry to show support for the RESULTS Act by contacting members of the Senate Finance, House Ways & Means and especially the House Energy & Commerce committees. The goal is to get the RESULTS Act inserted
into a broader healthcare package expected to be passed later this year.

ACLA has not finalized its estimate of what it thinks the RESULTS Act might cost. A critical factor to gaining passage is Congressional Budget Office (CBO) scoring. The understaffed CBO will need to be convinced that the RESULTS Act has a reasonable chance of passage before it devotes the time and resources to analyze its cost. A high-cost estimate from the CBO could doom passage into law. 

Without new legislation, Medicare CLFS rate cuts of up to 15% for roughly 800 lab tests will take effect on January 1, 2026. In addition, independent labs, hospital outreach labs and large POLs will be required to report their private-payer volume and payment data from 2019 for approximately 1,500 lab test codes by March 31, 2026. CMS will use this data to determine Medicare CLFS rates for 2027-2029.

The RESULTS Act would:

  • Freeze Medicare CLFS rates at current levels for 2026-2028.
  • Medicare CLFS rates for 2029-2032 would be based on weighted median private payer rates from January 1 – June 30, 2027.
  • Labs would no longer be required to report their private-payer payment data.
  • Data would be supplied to CMS from a claims database (including at least 50 billion lab claims from >50 private payers) from an independent nonprofit entity (e.g., The FAIR Health Database).
  • Rate cuts would be limited to 5% per year with no cap on rate increases.
  • Private-payer payment data would be collected and analyzed every 4 years (instead of 3 years).
  • Special reporting rules would apply to non-widely available lab test codes
    (100 or fewer labs perform) and for Advanced Diagnostic Lab Tests (ADLTs)

ACLA’s Van Meter says that the RESULTS Act removes the reporting burden from labs and would help ensure that all lag segments are accurately represented [especially highly reimbursed hospital outreach labs]. Lobbying efforts are being focused on committee members (Senate Finance and House Ways & Means and Energy & Commerce) because their support is necessary to advance the bill.

Previous efforts at PAMA reform, including the LAB Act (introduced 2019) and SALSA (introduced 2022), were unsuccessful primarily because of their estimated costs. For example, the CBO had estimated that passing SALSA into law would cost $6 billion over 10 years.

Over the past five years (2021-2025), Medicare CLFS rates have been frozen because of a series of one-year delays. Previously, the CBO had scored one-year delays to save money under the erroneous assumption that private payer lab test rates were increasing in line with inflation. However, the CBO is updating its forecasting model for the CLFS and another one-year freeze is unlikely.